Open Hours Tues - Fri 8:30 AM to 5:00 PM
Areas We Treat – Knee & Leg

Advanced Treatment for Knee & Leg Pain

Precision care for knee pain, leg injuries, arthritis, tendon and ligament conditions, instability, and post-surgical pain.

  • Physician-Led Evaluation & Treatment
  • Image-Guided Precision (Ultrasound & Fluoroscopy)
  • PRP & Autologous Biologic Options
  • Non-Surgical Care When Clinically Appropriate
Educational knee and lower-leg anatomy illustration with joint, ligament, meniscus, nerve, and diagnostic detail views
Overview

Understanding Knee and Leg Pain

The knee is one of the largest and most complex joints in the body. It bears weight, enables movement, and absorbs impact. Pain in the knee or leg can limit walking, running, climbing stairs, standing, and other daily activities.

Temporary medical illustration placeholder for knee joint and cartilage conditions
01

Joint, Cartilage & Meniscus Conditions

Knee osteoarthritis, chondromalacia, meniscal injury, avascular necrosis, and bone marrow edema can cause pain, swelling, stiffness, catching, and reduced function.

Temporary medical illustration placeholder for knee ligament injury and instability
02

Ligament Injury & Instability

Sprains or tears of the ACL, PCL, MCL, or LCL can affect knee stability, confidence, and movement, especially after twisting, contact, or overuse injuries.
Temporary medical illustration placeholder for knee tendon, bursa, and fat pad conditions
03

Tendon, Bursa & Soft-Tissue Pain

Patellar tendinopathy, iliotibial band syndrome, bursitis, Baker’s cyst, and Hoffa fat pad irritation may cause localized pain, swelling, or pain with loading.
Temporary medical illustration placeholder for nerve, bone, and post-surgical knee pain
04

Nerve, Bone & Post-Surgical Pain

Fabella-related pain, nerve entrapment, bone lesions, surgical hardware, or altered mechanics after a procedure can contribute to persistent knee or leg symptoms.

At Interventional Orthopedics of Washington, evaluation focuses on identifying whether symptoms arise from cartilage, ligaments, menisci, tendons, bursae, bone, nerves, hardware, or movement dysfunction so treatment can be matched to the most likely pain generator.

Conditions We Treat

Common Knee and Leg Conditions We Treat

We evaluate a wide range of acute, chronic, and post-surgical knee and leg conditions and recommend non-surgical treatment when it is clinically appropriate. These include:

Knee Joint, Cartilage & Ligament Conditions

Osteoarthritis of the Knee
ACL, PCL, MCL & LCL Sprains or Tears
Medial & Lateral Meniscal Tears
Patellar Tendinopathy (Jumper’s Knee)
Patellofemoral Pain & Chondromalacia
Iliotibial Band Syndrome (ITBS)
Knee Bursitis: Pes Anserine, Prepatellar, Infrapatellar & Suprapatellar

Bone, Bursa, Nerve & Post-Surgical Conditions

Hoffa Fat Pad Syndrome
Baker’s Cyst
Bone Marrow Edema
Avascular Necrosis of the Knee
Fabella Syndrome & Peripheral Nerve Entrapment
Post-Surgical Knee Pain

Whether pain comes from cartilage, ligaments, menisci, tendons, nerves, bursae, bone, surgical hardware, or movement dysfunction, the goal is to identify the most likely source and target treatment precisely.

Specialized Anatomy

Knee and Leg Areas We Specialize In

We use physical examination and image guidance, when appropriate, to evaluate and target major and supporting structures of the knee and leg, including:

Knee Joint & Stabilizing Structures

  • Ligaments: ACL, PCL, MCL, LCL, patellar retinaculum, and medial patellofemoral ligament
  • Menisci: Medial and lateral menisci with their meniscocapsular and coronary attachments
  • Intra-Articular Compartments: Patellofemoral, medial tibiofemoral, and lateral tibiofemoral compartments, synovium, and Hoffa fat pad
  • Patellar Structures: Patella, quadriceps tendon, patellar tendon, retinaculum, MPFL, and surrounding attachments
  • Bone Access Points: Femoral condyles, tibial plateaus, and patella when an imaging-confirmed bone target is present

Tendons, Bursae, Nerves & Post-Surgical Areas

  • Tendons: Patellar, quadriceps, biceps femoris, popliteus, and pes anserine tendons
  • Bursae: Prepatellar, superficial and deep infrapatellar, suprapatellar, and pes anserine bursae
  • Nerves: Genicular nerve branches, saphenous nerve, and common peroneal nerve
  • Lateral & Posterior Structures: Iliotibial band, lateral retinaculum, proximal tibiofibular region, popliteal region, and fabella
  • Around Surgical Hardware: Carefully selected pain after prior procedures once infection and mechanical complications have been excluded

This level of anatomic detail supports accurate diagnosis and image-guided treatment when a specific target and appropriate indication are present.

Evaluation & Treatment

Advanced Diagnostic Evaluation

Successful treatment begins with an accurate and comprehensive diagnosis. At IOW, evaluation may include:

  • In-depth physical examination and movement analysis
  • Review of prior imaging and advanced diagnostics as needed, including X-ray, MRI, and ultrasound
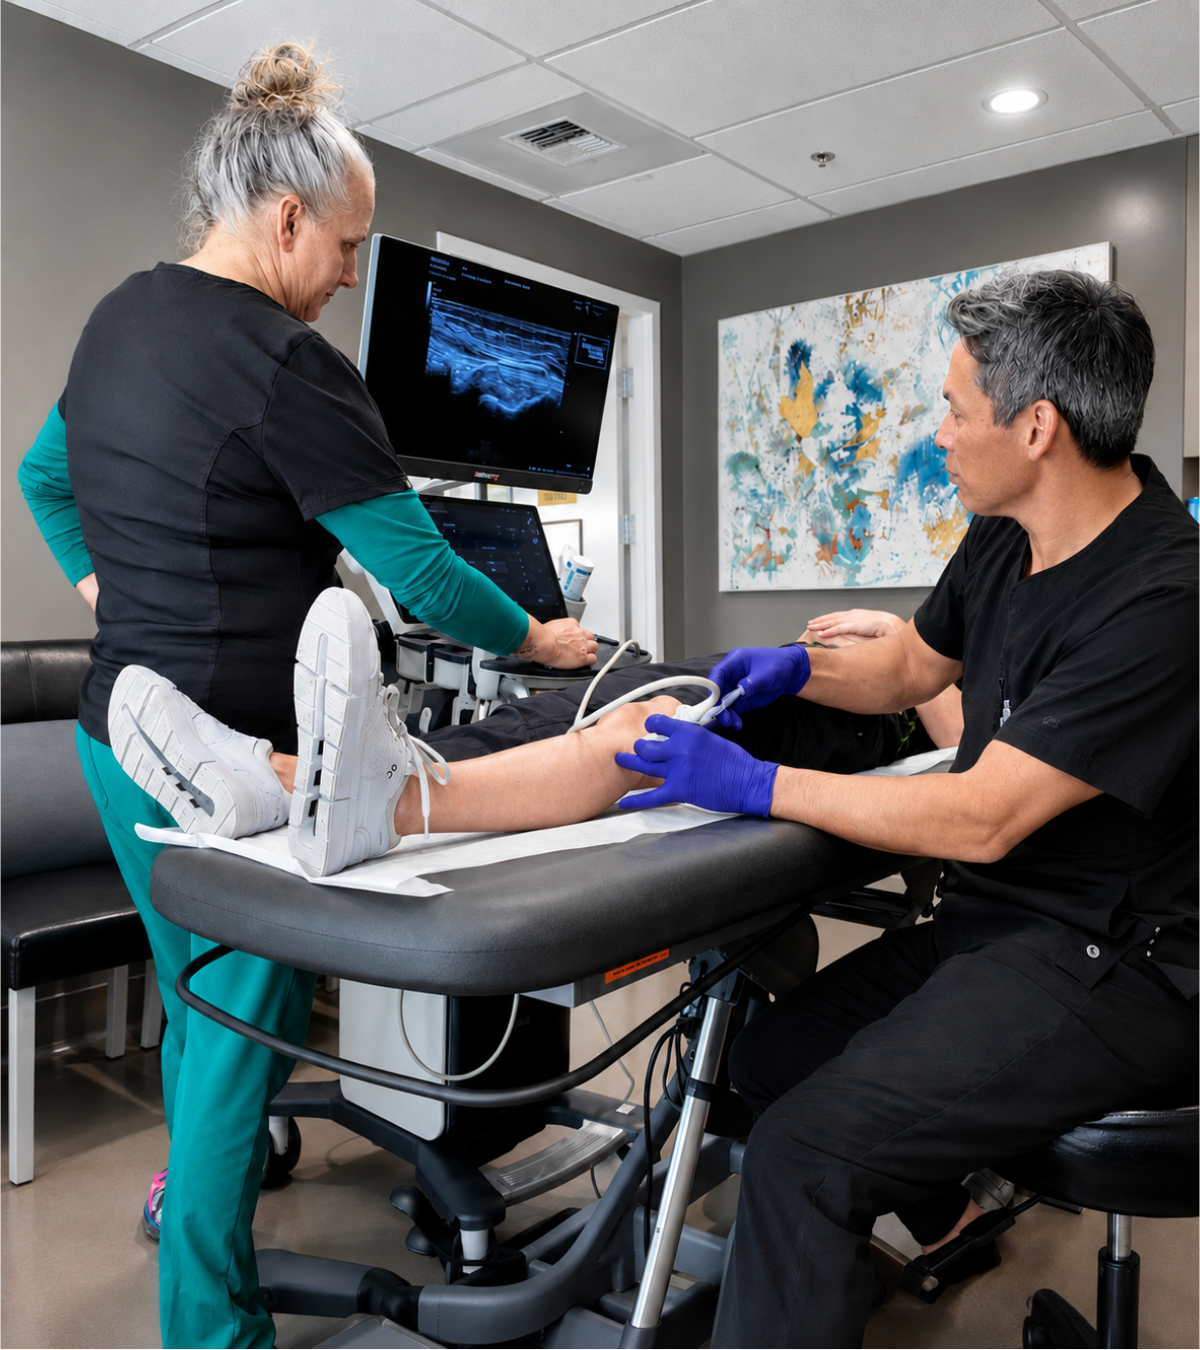
  • Real-time diagnostic musculoskeletal ultrasound when appropriate
  • Image-guided diagnostic injections or nerve blocks in selected cases to help localize pain sources

Diagnostic clarity allows us to create an individualized treatment plan focused on function, not just symptom reduction.

Regenerative Treatments

Types of Regenerative Treatments We Offer

Our non-surgical, image-guided options are selected according to the diagnosis, tissue involved, imaging findings, prior care, and available evidence. A treatment plan may include:

  • Image-Guided Prolotherapy: May be considered for selected ligament, tendon, or joint-related problems to stimulate a local healing response.
  • Image-Guided Platelet-Rich Plasma (PRP) Therapy: Uses concentrated platelets and growth factors from your own blood to support healing in selected tissues.
  • Autologous Bone Marrow Concentrate (BMC): May be considered in carefully selected cases involving cartilage, bone, ligament, or tendon pathology after review of the evidence, risks, and alternatives.
  • Baker’s Cyst or Joint Aspiration and Injection: May be used when a symptomatic fluid collection or joint effusion is confirmed and the procedure is appropriate.
  • Patellar Tendon or Peritendinous Hydrodissection: May be considered in selected cases when ultrasound identifies adhesions or restriction involving nearby tissue planes.
  • Hoffa Fat Pad Injection: May be considered when the examination and imaging support the fat pad as a pain generator.
  • Intraosseous Access to the Femur or Tibia: May be considered only for selected imaging-confirmed subchondral bone or marrow lesions.
Procedures are performed with ultrasound or fluoroscopic guidance when clinically appropriate. Outcomes vary, and no procedure guarantees tissue repair, pain relief, or avoidance of surgery.
Surgery Guidance

When Is Surgery Needed?

IOW prioritizes non-surgical care when it is safe, evidence-informed, and clinically appropriate. Some conditions, however, are best treated surgically or require prompt orthopedic evaluation.

  • Avoid unnecessary surgery when a reasonable nonoperative option exists
  • Use rehabilitation and orthobiologic options only when supported by the diagnosis
  • Support long-term function through progressive strengthening and follow-up
  • Refer promptly when fracture, infection, complete rupture, major instability, advanced degeneration, or another surgical problem is suspected

Surgery may be considered for severe structural damage, advanced arthritis, unstable fractures, complete ligament or tendon injuries, mechanical symptoms, infection, or persistent functional limitation despite appropriate conservative care. When surgical consultation is appropriate, we explain why and help coordinate referral.

Why Choose IOW

Why Choose IOW for Knee and Leg Treatment?

Choosing Interventional Orthopedics of Washington means receiving physician-led, diagnosis-first care designed around the most likely pain generator, your functional goals, and the most appropriate path forward.

  • Precision image guidance: Ultrasound or fluoroscopy is selected according to the treatment target and clinical need.
  • Complex orthopedic experience: Care includes evaluation of chronic, post-injury, and post-surgical knee conditions.
  • Whole-body biomechanics: We assess how the hip, pelvis, ankle, gait, and movement patterns influence knee function.
  • Minimally invasive options when appropriate: Non-surgical care is considered without delaying necessary surgical referral.
  • Personalized planning: Recommendations are tailored to your body, lifestyle, activity goals, prior care, and imaging findings.

Whether you are an athlete, an active adult, or recovering from a previous injury or procedure, the goal is to help you move with greater comfort and confidence.

Functional Comparison

Healthy Knee & Leg Function vs Painful or Unstable Function

Healthy Function

Stable, Well-Coordinated Knee & Lower-Limb Function

  • The knee joint, articular cartilage, and menisci help distribute load and support smooth bending, straightening, and weight-bearing movement
  • The ACL, PCL, MCL, LCL, joint capsule, and patellar stabilizers help control motion and maintain stability during walking, pivoting, and changes in direction
  • The quadriceps, hamstrings, calf, and hip muscles coordinate knee control, shock absorption, balance, and efficient movement during daily and athletic activity
  • Balanced mobility, strength, alignment, and load tolerance support comfortable walking, stairs, sitting, standing, running, and other daily activities
Painful or Unstable

Irritated, Injured, or Poorly Supported Knee & Leg

  • Osteoarthritis, chondromalacia, or meniscal injury may cause pain, swelling, stiffness, catching, locking, or reduced knee motion
  • ACL, PCL, MCL, or LCL injury may contribute to instability, swelling, reduced confidence, or a sensation that the knee may give way
  • Patellar or quadriceps tendon problems, iliotibial band syndrome, bursitis, Baker’s cyst, or Hoffa fat pad irritation may cause localized pain, swelling, or pain with loading
  • Bone marrow edema, osteonecrosis, peripheral nerve irritation, post-surgical changes, or altered hip and ankle mechanics may contribute to persistent symptoms and changes in gait
Treatment Protocol

Our 2-Step Approach to Knee & Leg Pain

A physician-led process that combines a detailed diagnostic evaluation with an individualized plan based on the suspected pain generator, physical examination, imaging, biomechanics, activity goals, prior care, and overall health.

1 · In-Office

Advanced Diagnostic Evaluation

Identifies the cartilage, meniscus, ligament, tendon, bursa, fat pad, bone, nerve, hardware, or movement pattern most likely contributing to your symptoms
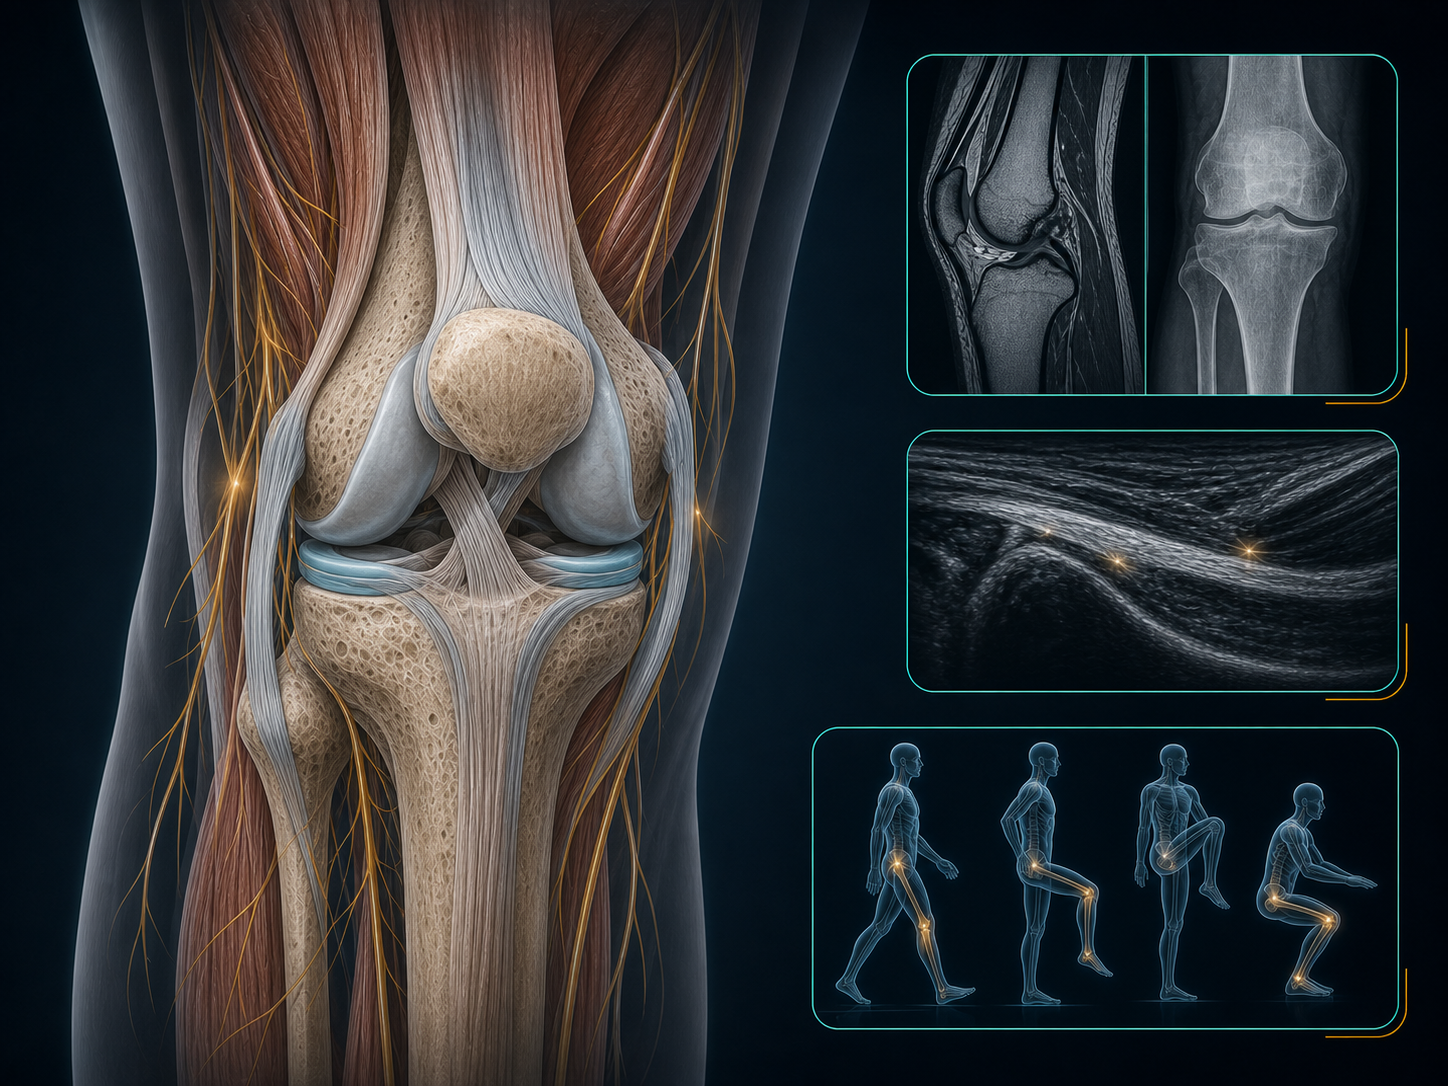
  • Review your medical history, symptom pattern, injury or surgical history, previous treatment, and activity goals
  • Perform a detailed knee and lower-extremity examination, including tenderness, swelling, range of motion, strength, ligament stability, meniscal findings, patellar mechanics, neurologic findings, and targeted provocative tests
  • Assess gait, lower-extremity alignment, hip and ankle mechanics, balance, movement control, and how symptoms change with activity or load
  • Review available X-rays, MRI, CT, ultrasound, or other prior imaging when clinically relevant, and recommend additional imaging only when it may change diagnosis or management
  • Use diagnostic musculoskeletal ultrasound and, in selected cases, image-guided aspiration, diagnostic injection, or nerve block when clinically appropriate and useful for localizing the pain source
Knee and leg evaluation illustration with joint anatomy, MRI, X-ray, ultrasound, and functional movement views
2 · Individualized Plan

Targeted Non-Surgical Treatment

Matches treatment to the diagnosis and most likely pain generator rather than simply treating the location of pain
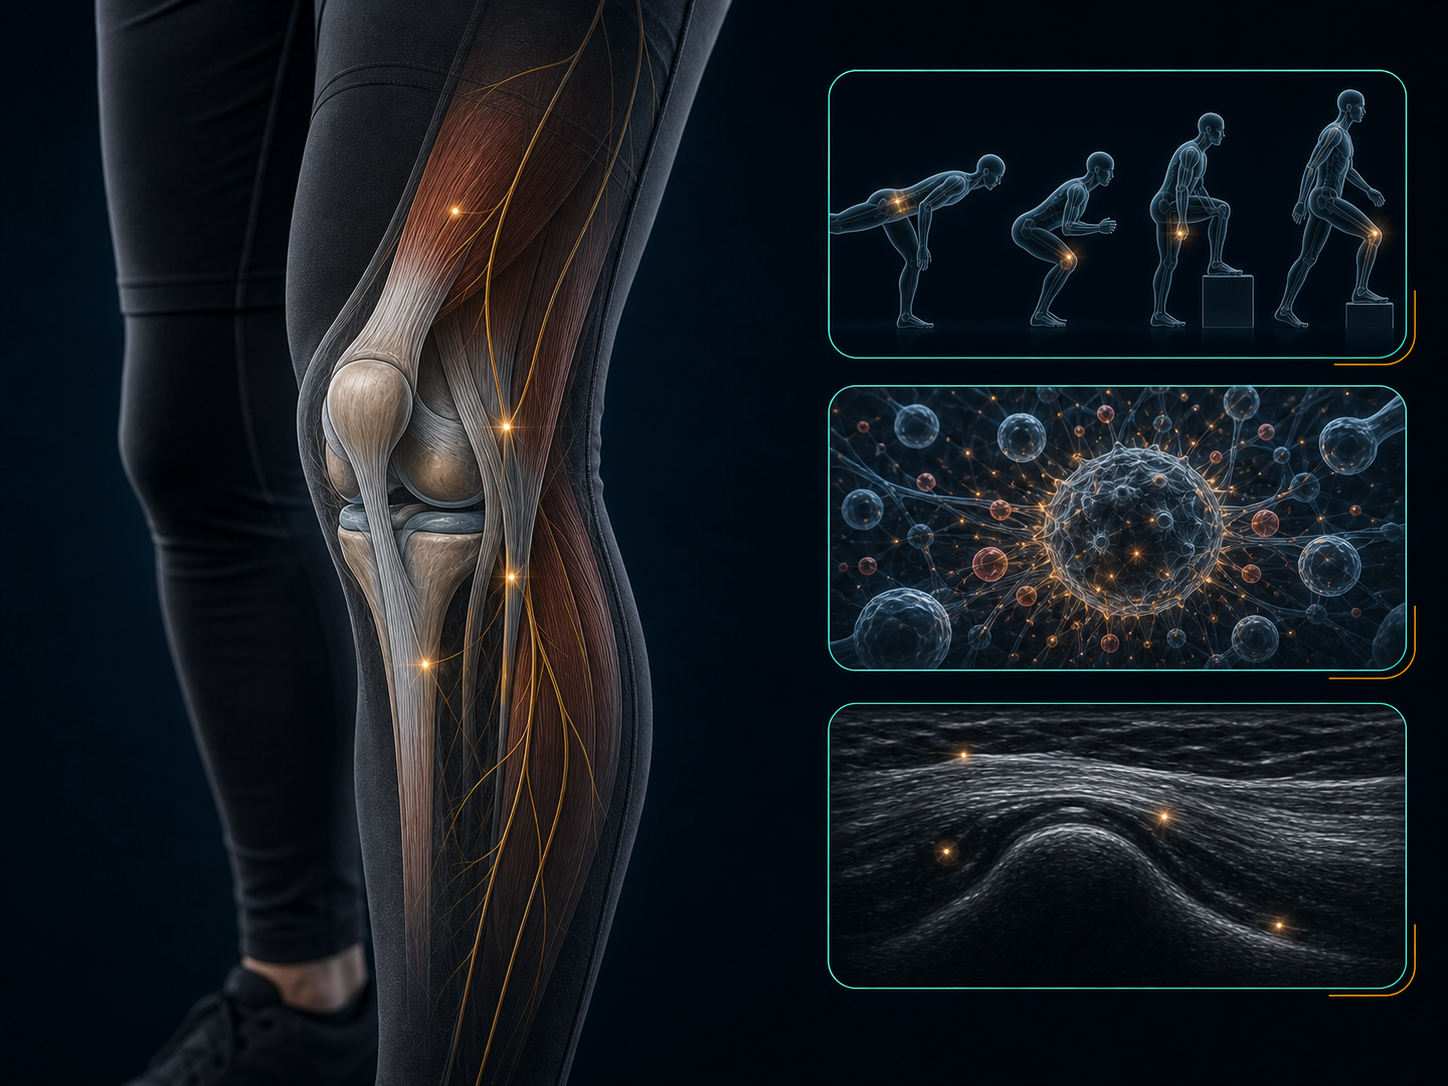
  • Rehabilitation and Load Management - may include activity modification, progressive quadriceps, hamstring, calf, hip, and core strengthening, mobility work, balance training, gait retraining, and gradual return to activity
  • Platelet-Rich Plasma (PRP) - may be considered for selected tendon, ligament, meniscal, or joint-related conditions after reviewing the diagnosis, available evidence, alternatives, risks, and expected recovery
  • Image-Guided Prolotherapy - may be discussed for carefully selected ligament, tendon, or instability-related knee conditions when the potential benefits, limitations, and alternatives are understood
  • Autologous Bone Marrow Concentrate (BMC) - may be discussed in carefully selected cartilage, subchondral bone, or joint cases after reviewing the uncertainties, alternatives, regulatory considerations, risks, recovery, and costs
  • Joint, Bursa, Cyst, Fat Pad, Nerve, or Bone-Targeted Procedures - may include image-guided joint aspiration or injection, Baker’s cyst or bursa procedures, Hoffa fat pad treatment, selected nerve blocks or hydrodissection, or intraosseous treatment when examination and imaging support a specific target
  • Specialist Referral - recommended when fracture, infection, complete tendon or ligament rupture, major instability, advanced degeneration, osteonecrosis with structural collapse, progressive neurologic findings, or a post-surgical mechanical complication requires different care
Individualized non-surgical knee treatment concept with anatomical targets, rehabilitation, healing biology, and ultrasound views

Precise diagnosis. Individualized treatment.

Not every knee or leg condition requires an injection or orthobiologic procedure. Because cartilage, meniscal, ligament, tendon, bursa, fat pad, bone, nerve, post-surgical, and biomechanical problems can produce overlapping symptoms, treatment is based on the most likely pain generator rather than symptoms alone. When a procedure is recommended, ultrasound or fluoroscopy is selected according to the treatment target and clinical need. Benefits, risks, alternatives, regulatory considerations, recovery expectations, and limitations are reviewed before treatment, and outcomes vary by condition and patient.

Who May Benefit

Who Should Consider a Knee & Leg Evaluation?

Persistent Pain Despite Appropriate Conservative Care

An evaluation may be helpful when knee or leg pain continues despite a reasonable trial of physical therapy, activity modification, progressive strengthening, load management, bracing, medication management, or other appropriate first-line care.

Post-Injury Pain, Swelling, Instability, or Mechanical Symptoms

This includes people with persistent symptoms after a fall, collision, twisting injury, sports injury, or previous knee procedure, as well as those who notice recurrent swelling, painful clicking, catching, giving way, weakness, or difficulty walking, climbing stairs, squatting, running, or standing.

Suspected Joint, Meniscus, Ligament, Tendon, Bone, or Nerve Pain

A detailed assessment may help when symptoms suggest knee osteoarthritis, a meniscal injury, ACL, PCL, MCL, or LCL injury, patellar or quadriceps tendinopathy, bursitis, Baker’s cyst, Hoffa fat pad irritation, bone marrow edema, avascular necrosis, iliotibial band syndrome, or peripheral nerve irritation.

Exploring Non-Surgical Options Before Elective Surgery

Patients considering arthroscopy, ligament reconstruction, meniscus surgery, osteotomy, or knee replacement may benefit from reviewing the diagnosis, imaging, rehabilitation options, and reasonable non-surgical treatments before deciding on the next step. Some injuries and advanced structural problems still require prompt orthopedic or surgical care.

Ready to Participate in Rehabilitation and Follow-Up

The best candidates understand that recovery often requires progressive knee, hip, and lower-extremity strengthening, gait or movement retraining, load management, and follow-up care. A procedure, when appropriate, is usually one part of a broader treatment plan.

The evaluation determines candidacy: not every knee or leg condition is appropriate for an injection or orthobiologic procedure. Acute fracture or dislocation, infection, a locked knee, complete tendon rupture, major instability, rapidly progressive weakness or numbness, suspected blood clot, advanced joint destruction, and other urgent or clearly surgical problems may require different care, emergency evaluation, or specialist referral.

Take the First Step

Could Non-Surgical Care Be Appropriate for Your Knee or Leg Pain?

Schedule an evaluation to review your symptoms, examination findings, knee and lower-extremity mechanics, previous treatment, and imaging. In-person care is recommended when a hands-on knee and leg examination, movement assessment, or diagnostic ultrasound is needed. Telemedicine may be available for an initial records and imaging review.

Know Your Options

Understanding Non-Surgical Care and When Surgery May Be Needed

Many knee and leg conditions are treated non-surgically first, while certain injuries, infections, mechanical problems, and advanced structural conditions require surgical care. The right sequence depends on the diagnosis, severity, stability, function, imaging findings, activity goals, and response to appropriate prior treatment.

Knee & Leg Surgical Considerations

  • Surgery may be appropriate for an acute fracture or dislocation, a locked or repairable meniscus tear, complete tendon rupture, major ligament instability, infection, osteonecrosis with structural collapse, or advanced arthritis causing substantial pain and functional limitation.12
  • Recovery varies by procedure and may involve walking aids, protected weight-bearing, bracing, activity restrictions, and structured rehabilitation over weeks or months.3
  • Knee arthroscopy may address selected meniscus tears, loose bodies, cartilage problems, or ligament injuries, but candidacy depends on the specific anatomy, symptoms, stability, cartilage condition, and response to nonoperative care.12
  • Total knee replacement may be considered for severe arthritis-related pain, stiffness, deformity, or disability when reasonable non-surgical treatments no longer provide adequate benefit. Implants can wear, loosen, become infected, or eventually require revision surgery.3
  • Potential risks vary by operation and can include infection, blood clots, nerve or blood-vessel injury, stiffness, loss of motion, nonunion, implant or hardware problems, and persistent pain. Surgical decisions should be made with an orthopedic surgeon after reviewing the expected benefits, limitations, alternatives, and recovery.

The IOW Diagnosis-First Approach

  • Care begins with a detailed history, knee and lower-extremity examination, stability and movement assessment, and review of clinically appropriate imaging to identify the most likely pain generator.
  • Initial care may include progressive knee and lower-extremity rehabilitation, strength and mobility work, gait or movement retraining, load management, bracing, activity modification, and medication management when appropriate.
  • Selected image-guided procedures may be considered when the diagnosis supports a specific knee joint, meniscus-adjacent, tendon, ligament, bursa, fat pad, subchondral bone, cyst, or peripheral nerve target.
  • PRP, prolotherapy, bone marrow concentrate, and other orthobiologic procedures are not interchangeable. Evidence, risks, recovery, regulatory status, and expected benefit vary by treatment and diagnosis.3
  • If surgery, fracture care, infection management, or another specialist is more appropriate, we explain why and coordinate referral rather than delaying necessary care.
Sources: 1. American Academy of Orthopaedic Surgeons. Meniscus Tears. OrthoInfo  |  2. American Academy of Orthopaedic Surgeons. ACL Injuries and Arthroscopy. OrthoInfo  |  3. American Academy of Orthopaedic Surgeons. Total Knee Replacement. OrthoInfo  |  4. American College of Radiology. Chronic Knee Pain. ACR Appropriateness Criteria  |  5. U.S. Food and Drug Administration. Important Patient and Consumer Information About Regenerative Medicine Therapies. FDA. This information is educational and is not a substitute for an individual medical evaluation.
The IOW Care Experience

Clear Answers, Individualized Care

Your visit begins with a diagnosis-focused evaluation rather than assuming that every knee or leg symptom comes from the same structure or should receive the same treatment.

Understand the Pain Generator

History · Knee and Leg Exam · Imaging · Biomechanics

Recommendations are explained in plain language, including expected benefits, limitations, alternatives, risks, recovery considerations, and when a procedure is not appropriate.

Make an Informed Decision

Transparent · Evidence-Informed · Patient-Centered

Treatment planning considers knee and lower-extremity rehabilitation, stability, mobility, gait mechanics, load tolerance, activity goals, and follow-up instead of relying on a procedure alone.

Build a Complete Recovery Plan

Rehabilitation · Progression · Follow-Up

These cards describe the care process and are not patient testimonials or promises of treatment outcome. Verified knee and leg reviews can be added here later without changing the section layout.

From the IOW Blog

Keep Learning About Knee & Leg Care

Explore IOW articles on PRP, rehabilitation, prolotherapy, orthobiologics, and non-surgical treatment planning relevant to knee osteoarthritis, meniscus and ligament injuries, patellar tendon conditions, and persistent knee or leg pain.
Frequently Asked Questions

Knee & Leg Regenerative Medicine FAQ

Answers to common questions about knee pain, leg injuries, joint degeneration, diagnostic evaluation, and non-surgical regenerative treatment options.

The knee absorbs a tremendous amount of stress during daily activities and sports. Pain can stem from issues with bones, cartilage, ligaments, tendons, nerves, or soft tissue, often due to injury, overuse, or joint degeneration.

Risk factors include high-impact sports, aging, obesity, repetitive kneeling or squatting, and prior injuries. Underlying health conditions like gout or lupus can also contribute to chronic knee discomfort.

We frequently treat ligament sprains like ACL or MCL injuries, meniscus tears, tendon damage, arthritis, and pain related to post-surgical complications. These injuries often affect stability and mobility across the entire leg.

Yes. Pain in the knee often links to surrounding structures like the hips, ankles, or low back. Dysfunction in one area can affect biomechanics throughout the body, which is why we take a full-body approach.

We combine movement analysis, physical exam, diagnostic ultrasound, and image-guided injections to pinpoint the source of pain. This ensures precise treatment for faster, more effective recovery.

Absolutely. Our regenerative treatments such as PRP, prolotherapy, and stem cell therapy stimulate natural healing and reduce inflammation without the need for invasive surgery.

Still dealing with knee or leg pain?

You might be a candidate for non-surgical, image-guided regenerative care. Schedule your free discovery call and let’s explore your options.

Schedule a Discovery Call

Medically reviewed by Dr. Otoño Silva, M.D.

Board Certified in Physical Medicine & Rehabilitation · Fellowship-Trained in Interventional Orthopedics, Centeno-Schultz Clinic

Last reviewed